Healthcare systems · Clinical AI · Autonomous ops
Nnamdi Okorafor
RN. Builder. The clinician who signs the system.
I harden AI-health products and infusion-scale operations so a credentialed nurse could put their name on them.

- Clinical nurse manager
- Ambulatory infusion
- Team
- 6 RNs
- Years
- 14 · ER, oncology, infusion
- Product
- Obioma · NCLEX Next Gen
Selected work
I run all of this through one agentic harness — isolated agent profiles, scheduled jobs, and a human approval gate on anything that leaves the building. Multiple projects, one operating cadence.
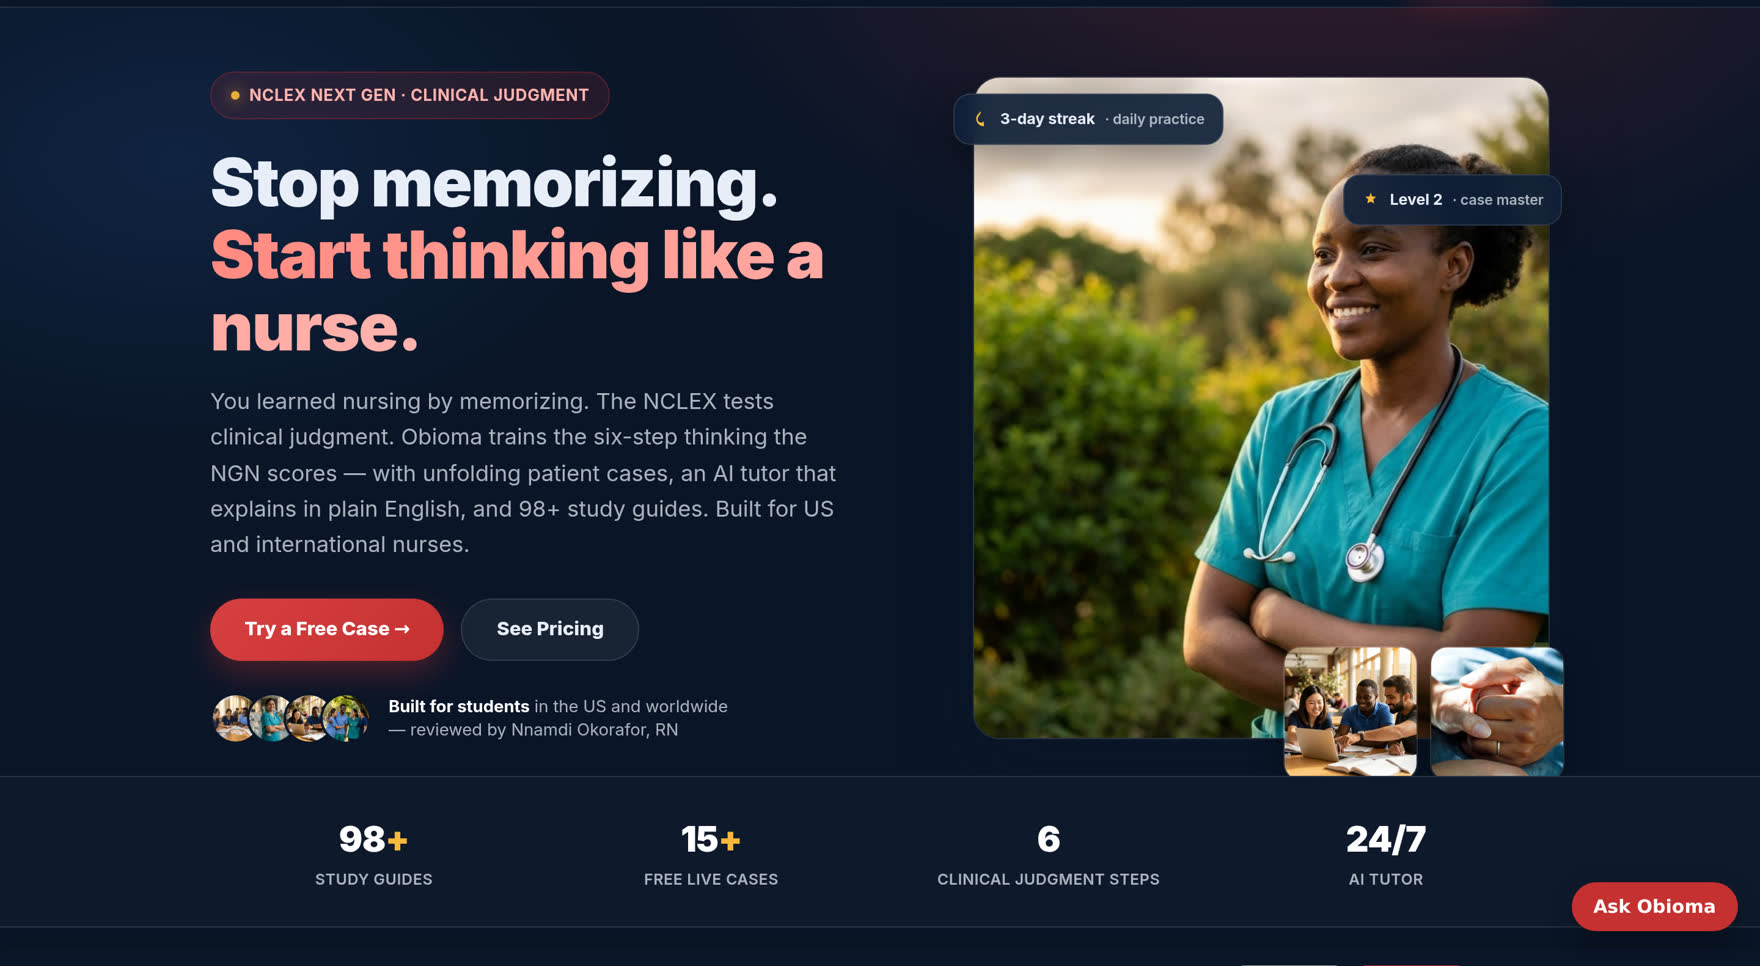
Obioma 2025–26
NCLEX Next Gen clinical-judgment platform. Six-step NCSBN reasoning with an AI tutor that teaches the miss, not the score.
Hermes agentic harness current
The system that runs the rest of this list. Named agents on separate profiles, recurring jobs on a schedule, and an approval gate before anything ships.
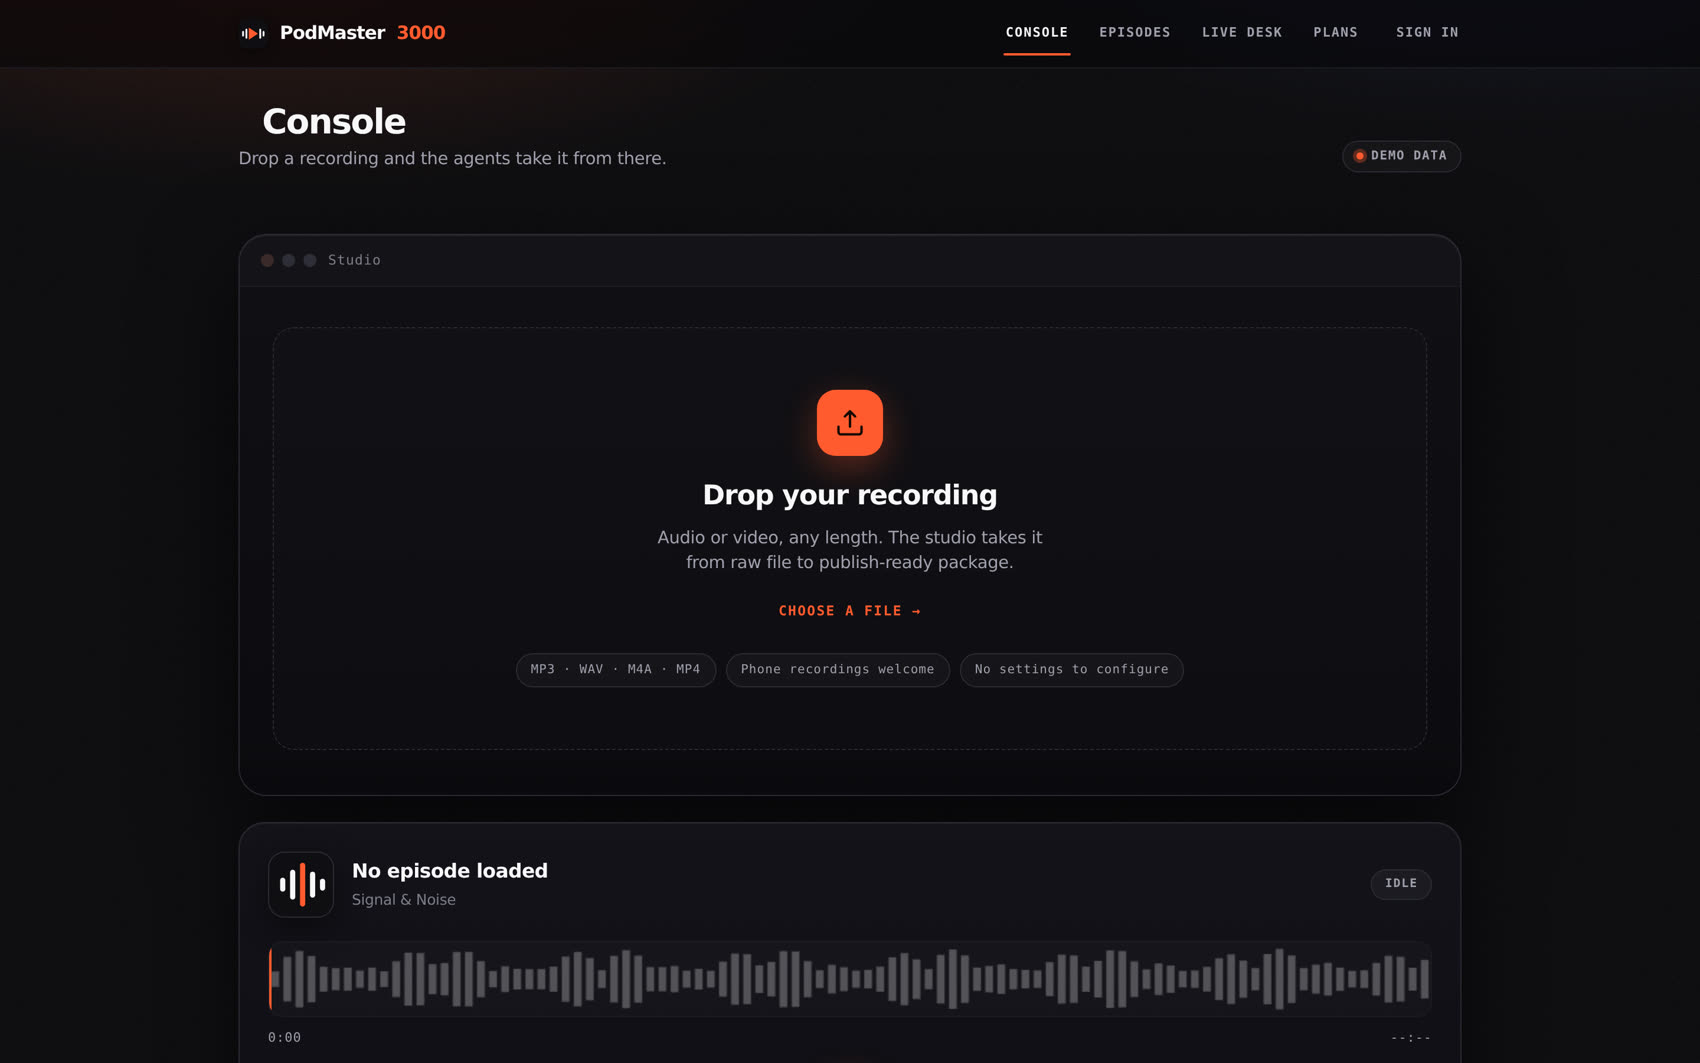
PodMaster3000 current
An AI podcast studio. Drop in a recording and the pipeline returns a publish-ready package. A QC gate hard-fails bad output and cannot be overridden.

Signal & Noise ongoing
My podcast. Long-form conversations on clinical work, systems and the business of healthcare — video first, because that is where the audience actually is.

The HCA Daily current
Clinical exam prep built with Dr. Ashley Hussain-Okorafor. Real drills, real rationales, no filler.
Infusion floor current
Staffing, throughput, capacity and AKS/Stark on a unit that runs every day. Where the operational instincts come from.
How to work together
Advisory
Fractional. I sit on the clinical-safety and eval story until a nurse could sign it.
$200 / hourOperations
Capacity, staffing model, AKS/Stark, and a 90-day plan. I run an infusion floor; I will audit yours.
$5–15k / engagementWriting
On burnout as a staffing model
Resilience is cheap to buy. A position is not.
Would a clinician sign this?
AI doesn’t fail loudly. It fails confidently.
Closed-loop ops
An agent that finishes a task beats a dashboard that reports on it.
About
I am a clinical nurse manager and I build systems. Fourteen years across ER, oncology and ambulatory infusion taught me where care actually breaks. Now I find the binding constraint — staffing, capacity, documentation, a safety story that will not hold — and build the loop that closes it. I do the same work for AI-health teams, where the stakes are identical: a real clinician has to sign it.
Let’s see if it signs.